|
Search Term: " 2026 "
NSAIDs vs. Curcumin: Which One Relieves Joint Pain Without Stopping Healing?   
Date:
September 14, 2026 11:22 AM
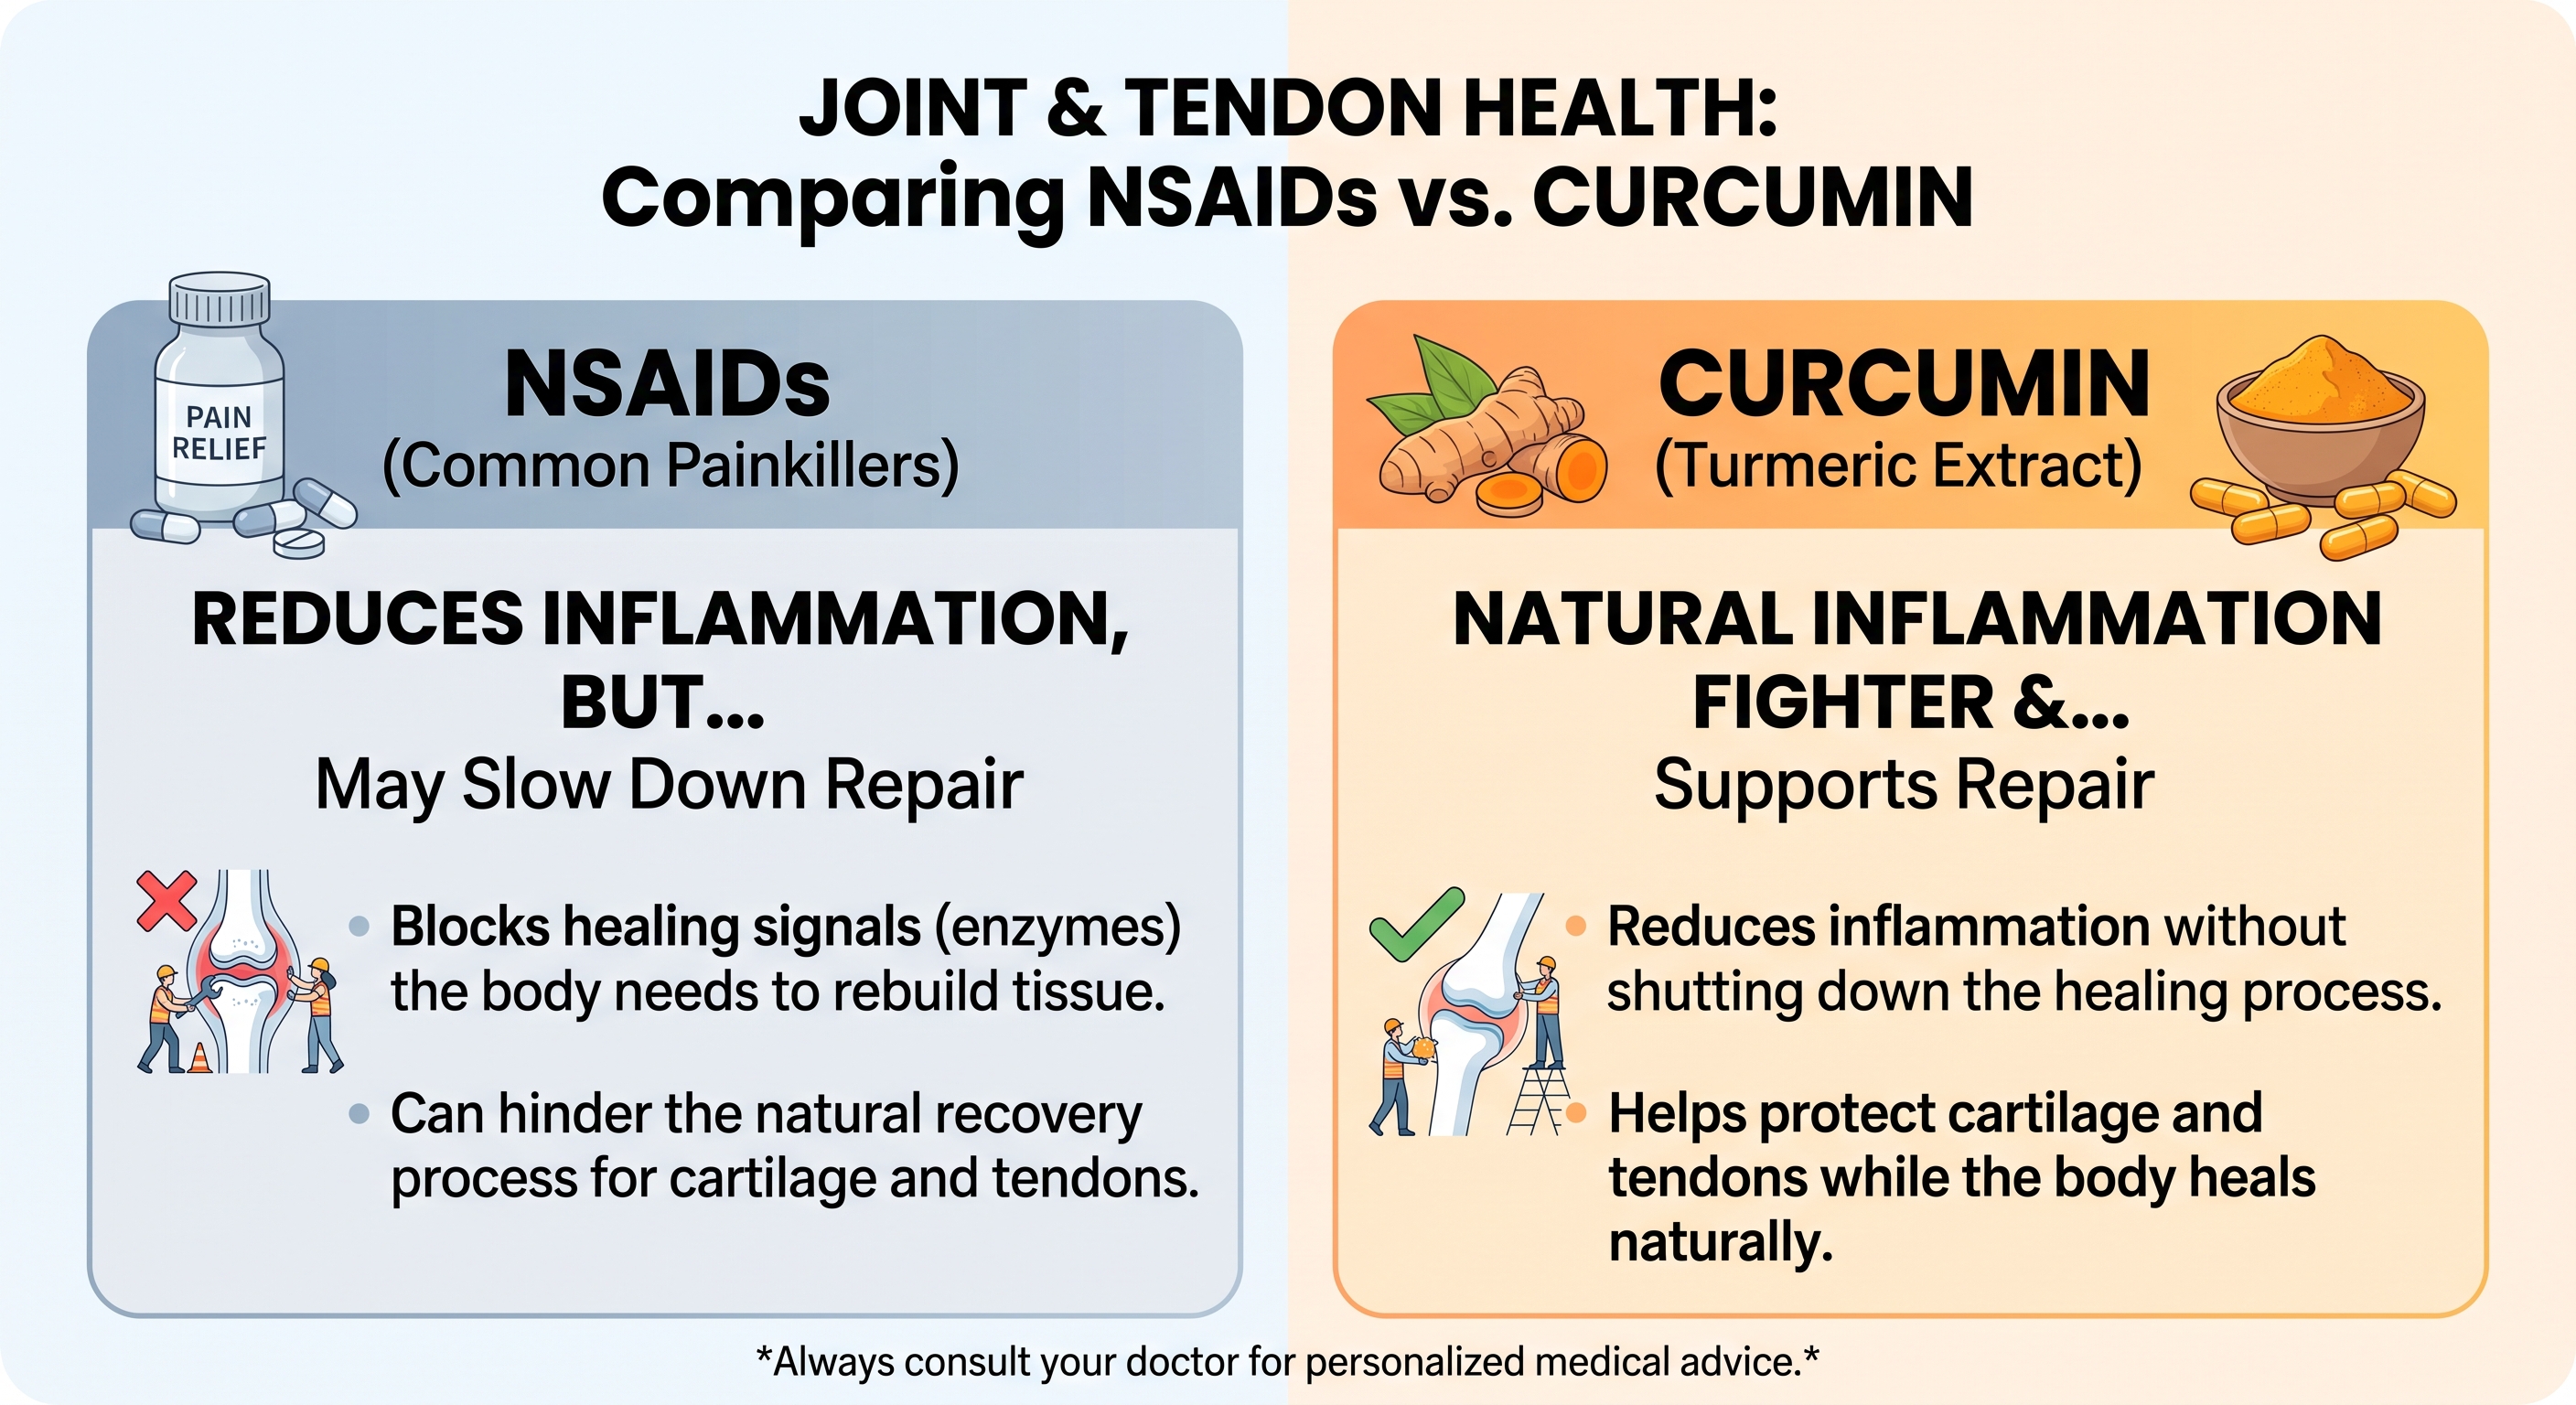
Comparative Analysis of NSAIDs versus Curcumin in Musculoskeletal Tissue RepairPrimary Biological Mechanisms and Pharmacological TargetsManaging soft tissue and joint injuries presents a persistent therapeutic challenge in musculoskeletal medicine. Acute inflammation triggers pain, localized swelling, and mechanical disability, which routinely drives patients toward pharmacological relief. For decades, nonsteroidal anti-inflammatory drugs (NSAIDs) such as ibuprofen, naproxen, celecoxib, and diclofenac have served as primary clinical interventions. While these synthetic agents effectively extinguish acute pain signals, expanding cellular and clinical research indicates that their biochemical mechanism interrupts the fundamental repair cascades required for long-term connective tissue healing. In contrast, curcumin - a natural polyphenolic compound derived from the rhizomes of Curcuma longa (turmeric) - exhibits a distinct, multi-targeted regulatory profile that calms hyperactive inflammation while protecting the structural components of cartilage and tendon tissue.The functional divergence between these two compounds becomes clear when considering an intuitive mechanical analogy. Tissue trauma resembles damage to a commercial building, where initial inflammation functions as the construction and demolition crew tasked with clearing rubble, stabilizing the foundation, and laying down fresh structural framing. NSAIDs function like abruptly cutting electrical power to the entire work site: the noisy machinery stops instantly and the immediate disturbance ceases, but the construction workers lose the power necessary to clean the debris and erect permanent walls. Conversely, curcumin operates as an experienced site manager: it silences unnecessary chaos and prevents site vandalism while ensuring that the skilled workers - specifically chondrocytes in cartilage and tenocytes in tendons - remain fully active, supplied, and capable of completing the restoration. At the cellular level, NSAIDs exert their effects through the catalytic inhibition of cyclooxygenase enzymes, categorized as constitutive cyclooxygenase-1 (COX-1) and inducible cyclooxygenase-2 (COX-2). Membrane phospholipids damaged during injury release arachidonic acid, which COX enzymes convert into pro-inflammatory lipid mediators known as prostanoids, most notably prostaglandin E2 (PGE2). Nonselective NSAIDs block both isoforms, while selective coxibs specifically target COX-2. By shutting off PGE2 production, NSAIDs rapidly elevate pain thresholds and blunt localized swelling. However, because PGE2 also functions as a vital signaling cue for cellular recruitment, angiogenesis, and cellular proliferation, this total enzymatic shutdown strips local repair cells of the baseline signals required to orchestrate tissue regeneration. Curcumin avoids this indiscriminate pathway paralysis by acting upstream on master transcriptional control switches rather than directly neutralizing isolated enzymes. Its primary therapeutic mechanism centers on the inhibition of Nuclear Factor-kappa B (NF-kB) and Activator Protein-1 (AP-1) signaling networks. Under acute stress or chronic inflammatory loads, the NF-kB protein complex is released from its cytoplasmic inhibitor, IkBa, and translocates directly into the cell nucleus, where it drives the transcription of catabolic cytokines such as interleukin-1 beta (IL-1ß), tumor necrosis factor-alpha (TNF-a), and interleukin-6 (IL-6). Curcumin blocks the phosphorylation and degradation of IkBa, effectively keeping NF-kB trapped in the cytoplasm. By preventing this nuclear entry, curcumin attenuates the expression of pro-inflammatory cytokines and downstream matrix-degrading enzymes while preserving baseline physiological functions. Furthermore, curcumin activates the nuclear factor erythroid 2-related factor 2 (Nrf2) and antioxidant response element (ARE) pathways, which upregulate endogenous cellular antioxidants to neutralize destructive reactive oxygen species (ROS) that induce cell death in injured joints.
The Mechanisms of NSAID-Induced Inhibition in Cartilage and Tendon RepairArticular cartilage and tendons are specialized, bradytrophic connective tissues characterized by relatively low basal metabolic rates and limited endogenous vascular supplies. These physical constraints make their cellular maintenance highly vulnerable to pharmaceutical disruptions. When synthetic compounds impair cell migration, survival, or extracellular matrix secretion, the intrinsic repair capacity of these structures is substantially degraded.Cartilage maintenance depends on chondrocytes, the sole cell type residing within articular joints, which are responsible for generating and maintaining the extracellular matrix of Type II collagen and water-binding proteoglycans such as aggrecan. Because adult articular cartilage lacks a direct vascular network, major defect repair relies heavily on the recruitment and chondrogenic differentiation of subchondral mesenchymal stem cells (MSCs) through endochondral ossification. Experimental evaluations demonstrate that systemic or intra-articular NSAID exposure halts this regenerative differentiation. Both nonselective NSAIDs and selective COX-2 inhibitors interfere with chondrocyte maturation and prevent successful tissue integration following cartilage transplantation or microfracture procedures. At the cellular level, common NSAIDs - including indomethacin, ketorolac, and diclofenac - induce cell cycle arrest in chondrocytes by blocking transition from the resting G0 phase to the proliferative G1. phase, substantially reducing viable cell numbers. Concurrently, NSAIDs downregulate Bone Morphogenetic Protein-2 (BMP-2), an essential anabolic signaling molecule that orchestrates matrix synthesis. Histological analyses in animal models reveal that NSAID administration causes a marked loss of extracellular proteoglycan content and widespread chondrocyte depletion, yielding elevated modified Mankin scores that signify advanced structural degeneration. In layman's terms, proteoglycans serve as water-absorbing structural sponges that grant cartilage its elastic shock absorption. When NSAIDs deplete these molecules, the joint surface dries out, becomes brittle, and rapidly wears down under routine mechanical friction. Tendon healing is similarly susceptible to disruption by NSAIDs. Tendons operate as high-tensile structural cables composed of longitudinally arranged Type I collagen fibers, maintained by specialized fibroblasts termed tenocytes and tenoblasts. Healing after acute rupture or chronic tear progresses through an initial inflammatory phase, followed by a proliferative phase of cell migration, and culminates in a lengthy remodeling phase of collagen alignment. In vitro and in vivo studies establish that NSAIDs directly suppress the migration and proliferative capacity of tenocytes during the critical early healing window. Without an adequate cellular workforce migrating into the wound bed, provisional collagen scaffolding cannot be synthesized effectively. The disruption is particularly pronounced at the enthesis, the specialized fibrocartilaginous junction where soft tendon inserts into rigid bone. Re-establishing this transition zone requires coordinated bone remodeling and chondrogenic differentiation, both of which are hindered by COX inhibition. In animal rotator cuff repair models, early administration of NSAIDs significantly delays collagen fiber organization and impairs mechanical integration at the insertion site, resulting in a measurable decline in load-to-failure strength and overall tendon toughness. Furthermore, while prolonged inflammation contributes to pathological degeneration, the transient synthesis of PGE2 during the initial hours following injury is essential for regulating localized microvascular flow and hyperemic nutrient delivery. By eliminating this early prostanoid pulse, NSAIDs starve the repair zone of oxygen and circulating factors precisely when the cellular metabolic demand is highest. Beyond direct biochemical cytotoxicity, systemic NSAIDs introduce a physical hazard known as analgesic arthropathy. In musculoskeletal biomechanics, pain functions as a protective feedback mechanism, forcing the patient to unload an injured joint or limb to prevent structural overload. By effectively blunting the pain reflex while simultaneously undermining the cellular synthesis of proteoglycans and collagen, NSAIDs create a deceptive state of perceived recovery. Patients prematurely resume unrestricted weight-bearing and strenuous activity, placing substantial, uncompensated mechanical forces onto compromised cartilage surfaces and unhealed tendon fibers. Over time, this recurring mechanical trauma accelerates joint space narrowing, promotes microfractures in the subchondral plate, and hastens functional joint breakdown. Chondroprotective and Tenogenic Mechanisms of CurcuminIn sharp contrast to the suppressive actions of synthetic COX inhibitors, curcumin exhibits a tissue-sparing, pro-regenerative biological profile. Rather than paralyzing cellular metabolism, curcumin modulates the microenvironment by suppressing destructive catabolic enzymes while supporting the baseline anabolic signals required for cartilage and tendon reconstruction.In articular cartilage, curcumin acts as a direct chondroprotective agent by dismantling the catabolic cascade induced by pro-inflammatory cytokines. When joint tissues are exposed to elevated IL-1ß and TNF-a, chondrocytes are provoked to synthesize matrix metalloproteinases - specifically collagenases such as MMP-1, MMP-3, and MMP-13 - along with aggrecanases like ADAMTS5. These enzymes function like enzymatic shears, systematically slicing through structural Type II collagen strands and degrading aggrecan cores. Curcumin suppresses the transcription and secretion of MMP-1, MMP-3, MMP-13, and ADAMTS5 by neutralizing NF-kB and AP-1 activation. Concurrently, it upregulates Cbp/p300 Interacting Transactivator with ED-rich tail 2 (CITED2), an essential transcriptional regulator that represses matrix metalloproteinases at the genomic level. In addition to halting extracellular degradation, curcumin protects chondrocytes from inflammatory apoptosis. Exposure to oxidative stress and inflammatory cytokines typically triggers programmed cell death by activating the intrinsic caspase cascade. Curcumin suppresses this apoptotic pathway by reducing the cleavage of executioner caspase-3, downregulating the pro-apoptotic factor Bax, and elevating anti-apoptotic Bcl-2 expression. Microscopic and histological analyses of osteoarthritic cartilage treated with curcumin consistently show robust Safranin O staining, intact surface regularity, preserved chondrocyte density, and significantly reduced Osteoarthritis Research Society International (OARSI) degradation scores. Within tendon biology, curcumin promotes active tissue regeneration (tenogenesis) rather than inert scar formation. In animal models of tendon rupture and surgical repair, curcumin guides tendon-derived stem and progenitor cells (TSPCs) toward mature tenocyte differentiation. This lineage-specific differentiation is orchestrated primarily through activation of the phosphatidylinositol 3-kinase/protein kinase B (PI3K/Akt) and Wnt/ß-catenin signaling cascades. As stem cells commit to the tenogenic pathway, they significantly upregulate crucial structural and phenotypic markers, including epithelial cell adhesion molecule (EpCAM), tenomodulin, and the master tendon transcription factor Scleraxis. Through this guided differentiation, curcumin supports the preferential synthesis and organized deposition of high-tensile Type I collagen fibers, the primary architectural building blocks of healthy tendons. Injured tendons typically fill with disorganized, loose Type III collagen, which forms a structurally inferior, compliant scar. Curcumin supplementation promotes the progressive maturation from primitive Type III collagen to densely packed, parallel Type I collagen fibrils, restoring native tensile strength and mechanical breaking force. A major clinical challenge following tendon surgery is the development of peritendinous adhesions, in which excessive fibrotic scar tissue binds the healing tendon to its synovial sheath, restricting range of motion and joint gliding. Postoperative tendon repair involves a balance between extrinsic healing (in which exterior fibroblasts infiltrate the defect and deposit messy scar tissue) and intrinsic healing (in which tenocytes within the tendon substance reconstruct the matrix). Curcumin suppresses excessive peritendinous inflammation and extrinsic fibrosis while accelerating intrinsic tenocyte repair. Biomechanical testing confirms that local or systemic curcumin administration yields lower adhesion scores, increased gliding distances, and superior functional mobility without sacrificing structural load-bearing capacity. Comparative Clinical Efficacy and Systemic Safety ProfilesTranslating cellular findings into clinical practice requires weighing therapeutic outcomes against systemic safety profiles. While synthetic NSAIDs deliver potent, rapid analgesia during acute musculoskeletal pain events, their chronic administration is constrained by systemic toxicities across multiple organ systems.In randomized, active-controlled clinical trials of knee osteoarthritis, optimized curcumin preparations have demonstrated clinical pain reduction and functional recovery comparable to standard therapeutic doses of NSAIDs. In a randomized, open-label parallel-arm study evaluating 139 patients with symptomatic knee osteoarthritis, subjects received either 500 mg of a bio-enhanced curcumin extract three times daily or 50 mg of diclofenac sodium twice daily for 28 consecutive days. Patients treated with curcumin demonstrated comparable improvements in pain intensity on the Visual Analogue Scale (VAS) and functional scores on the Knee Injury and Osteoarthritis Outcome Score (KOOS) at days 14 and 28, showing no statistically significant difference in therapeutic efficacy compared to diclofenac. However, the systemic tolerability profiles between the treatments diverged markedly. Overall adverse events occurred in only 13% of the curcumin group compared to 38% of the diclofenac cohort. In the diclofenac arm, 28% of patients developed dyspeptic symptoms severe enough to require concurrent treatment with H2-receptor antagonists or proton pump inhibitors to prevent mucosal ulceration, whereas no patients in the curcumin cohort required gastroprotective intervention. Furthermore, the curcumin cohort experienced a significant reduction in flatulence and digestive discomfort, demonstrating beneficial gastric and intestinal cytoprotective effects. These safety observations are consistent across broader systematic reviews and meta-analyses. Nonsteroidal anti-inflammatory agents inherently compromise gastrointestinal integrity by systematically depleting cytoprotective prostaglandins, leaving the gastric epithelium vulnerable to acid erosion and hemorrhage. In addition, systemic inhibition of renal and vascular COX enzymes by NSAIDs reduces renal perfusion and disrupts the balance between prostacyclin and thromboxane, elevating the risk of fluid retention, hypertension, and adverse cardiovascular thrombotic events. Curcumin does not suppress these physiological prostanoid pathways, making it free from ulcerogenic, nephrotoxic, and cardiotoxic properties at therapeutic dosages.
A longstanding limitation of standard curcumin supplementation in clinical settings has been its low oral bioavailability. Native curcuminoids are highly lipophilic, poorly soluble in aqueous gastric fluids, and subject to rapid hepatic and intestinal phase II metabolism into inactive glucuronides and sulfates, leading to swift biliary and fecal excretion. Consequently, raw culinary turmeric powders struggle to achieve the therapeutic systemic circulating concentrations required to reach poorly vascularized joint and tendon compartments. Modern pharmacognosy has addressed this pharmacodynamic hurdle through advanced delivery formulations. Modern strategies - such as co-administration with the natural alkaloid piperine (which inhibits hepatic glucuronidation), micellar dispersions, phytosomal phospholipid complexes, and bio-enhanced submicron dispersions - elevate systemic blood bioavailability by ten- to thirty-fold compared to unformulated extracts. These modern delivery platforms ensure that therapeutic concentrations reach synovial fluid, subchondral bone, and fibrous tendon sheaths without requiring excessive oral dosing. Conclusions and Translational Clinical ImplicationsThe biological and clinical evidence reveals distinct physiological paths for NSAIDs and curcumin in orthopedic recovery. While NSAIDs remain powerful tools for the brief alleviation of acute, unmanageable pain, their ongoing administration during active tissue healing presents substantial biological compromises. Tendons and cartilage require a controlled, transient inflammatory cascade to signal cell recruitment, stimulate stem cell differentiation, and direct extracellular matrix synthesis. By completely shutting down cyclooxygenase enzymes and depleting local prostaglandins, NSAIDs disrupt this regenerative cascade. The resulting cellular consequences - including chondrocyte cell cycle arrest, proteoglycan loss, suppression of tenocyte migration, and weakened collagen tensile strength at the tendon-to-bone interface - demonstrate that pain relief from NSAIDs frequently comes at the cost of the structural integrity of healing connective tissues.In contrast, curcumin provides a tissue-preserving alternative that decouples pain and inflammation control from cellular suppression. Operating upstream at the level of NF-kB and AP-1 transcriptional activation, curcumin attenuates the expression of pro-inflammatory cytokines while leaving the physiological baseline of cellular metabolism intact. In cartilage, it actively represses the matrix-degrading enzymes MMP-1, MMP-3, MMP-13, and ADAMTS5, maintains water-binding proteoglycan content, and protects chondrocytes from inflammatory apoptosis. In damaged tendons, curcumin stimulates tenogenic differentiation of local stem cells via PI3K/Akt signaling, supports the proper maturation of dense Type I collagen fibers, and prevents restrictive peritendinous scar adhesions, preserving both joint mobility and mechanical breaking strength. From a translational perspective, these findings indicate that clinical protocols should reconsider relying on continuous NSAIDs as the default intervention for connective tissue injuries, post-surgical recovery, and chronic degenerative conditions. Where synthetic NSAIDs are deemed necessary, their use should be confined to short-term acute flare-ups to avoid interrupting early tissue remodeling. For long-term joint preservation, ongoing tendinopathy rehabilitation, and chronic osteoarthritis management, optimized bio-enhanced curcumin formulations deliver pain relief and functional restoration comparable to conventional pharmaceuticals, all while preserving the biological processes required for lasting musculoskeletal repair. References: NSAID therapy effects on healing of bone, tendon, and the enthesis The Detrimental Effects of Systemic Ibuprofen Delivery on Tendon Conservative management of symptomatic knee osteoarthritis - PMC Positives and negatives of nonsteroidal anti-inflammatory drugs in (PDF) Conservative management of symptomatic knee osteoarthritis Non-steroidal anti-inflammatory drugs influence cartilage healing Is Curcumine Useful in the Treatment and Prevention of ... - PMC - NIH Efficacy and mechanisms of curcumin in the treatment of osteoarthritis Biological actions of curcumin on articular chondrocytes - PubMed Curcumin slows osteoarthritis progression and relieves ... - PMC - NIH Do Nonsteroidal Anti-Inflammatory Drugs Have a Deleterious Effect Anti-inflammatory management for tendon injuries - friends or foes? The mechanistic role of curcumin on matrix metalloproteinases in Therapeutic effects of turmeric or curcumin extract on pain and Curcumin inhibits chondrocyte apoptosis and inflammation in ... - PMC Analysis of the mechanism of curcumin against osteoarthritis using Synergistic enhancement of tendon-to-bone healing via anti ... - PMC A Multicenter, Randomized, Double-Blind, Placebo-Controlled Trial Safety and efficacy of curcumin versus diclofenac in knee osteoarthritis A randomized, pilot study to assess the efficacy and safety ... - PubMed Effectiveness of curcuminoids in the treatment of knee osteoarthritis THE EFFECTS OF TRADITIONAL STRENGTHENING EXERCISES Putting Some Muscle into Osteoarthritis | Annals of Internal Medicine Do Nonsteroidal Anti-Inflammatory Drugs Have a Deleterious Effect Calebin A, a Compound of Turmeric, Down-Regulates Inflammation The Effect of Non-Steroidal Anti-Inflammatory Drugs on Tendon-to Chiropractor in Toronto, ON, Canada :: Head and Neck Pain Investigation of the association of long-term NSAID use with ... - PMC Curcumin Improves Functional Recovery of Ruptured Tendon by Chemically modified curcumin (CMC2.24) alleviates osteoarthritis Curcumin improves age-related and surgically induced osteoarthritis (PDF) Curcumin Improves Functional Recovery of Ruptured Tendon Investigation of the effects of umbilical cord-derived mesenchymal Effect of curcumin-loaded polycaprolactone scaffold on Achilles Controlled release of curcumin from curcumin-loaded nanomicelles Efficacy and safety of combination of curcuminoid complex ... - PMC The efficacy of Curcuma Longa L. extract as an adjuvant therapy in
(https://vitanetonline.com:443/forums/Index.cfm?CFApp=1&Message_ID=6653) Is NAD+ the "Missing Link" in Modern Longevity Science? 
Date:
April 11, 2026 12:24 PM
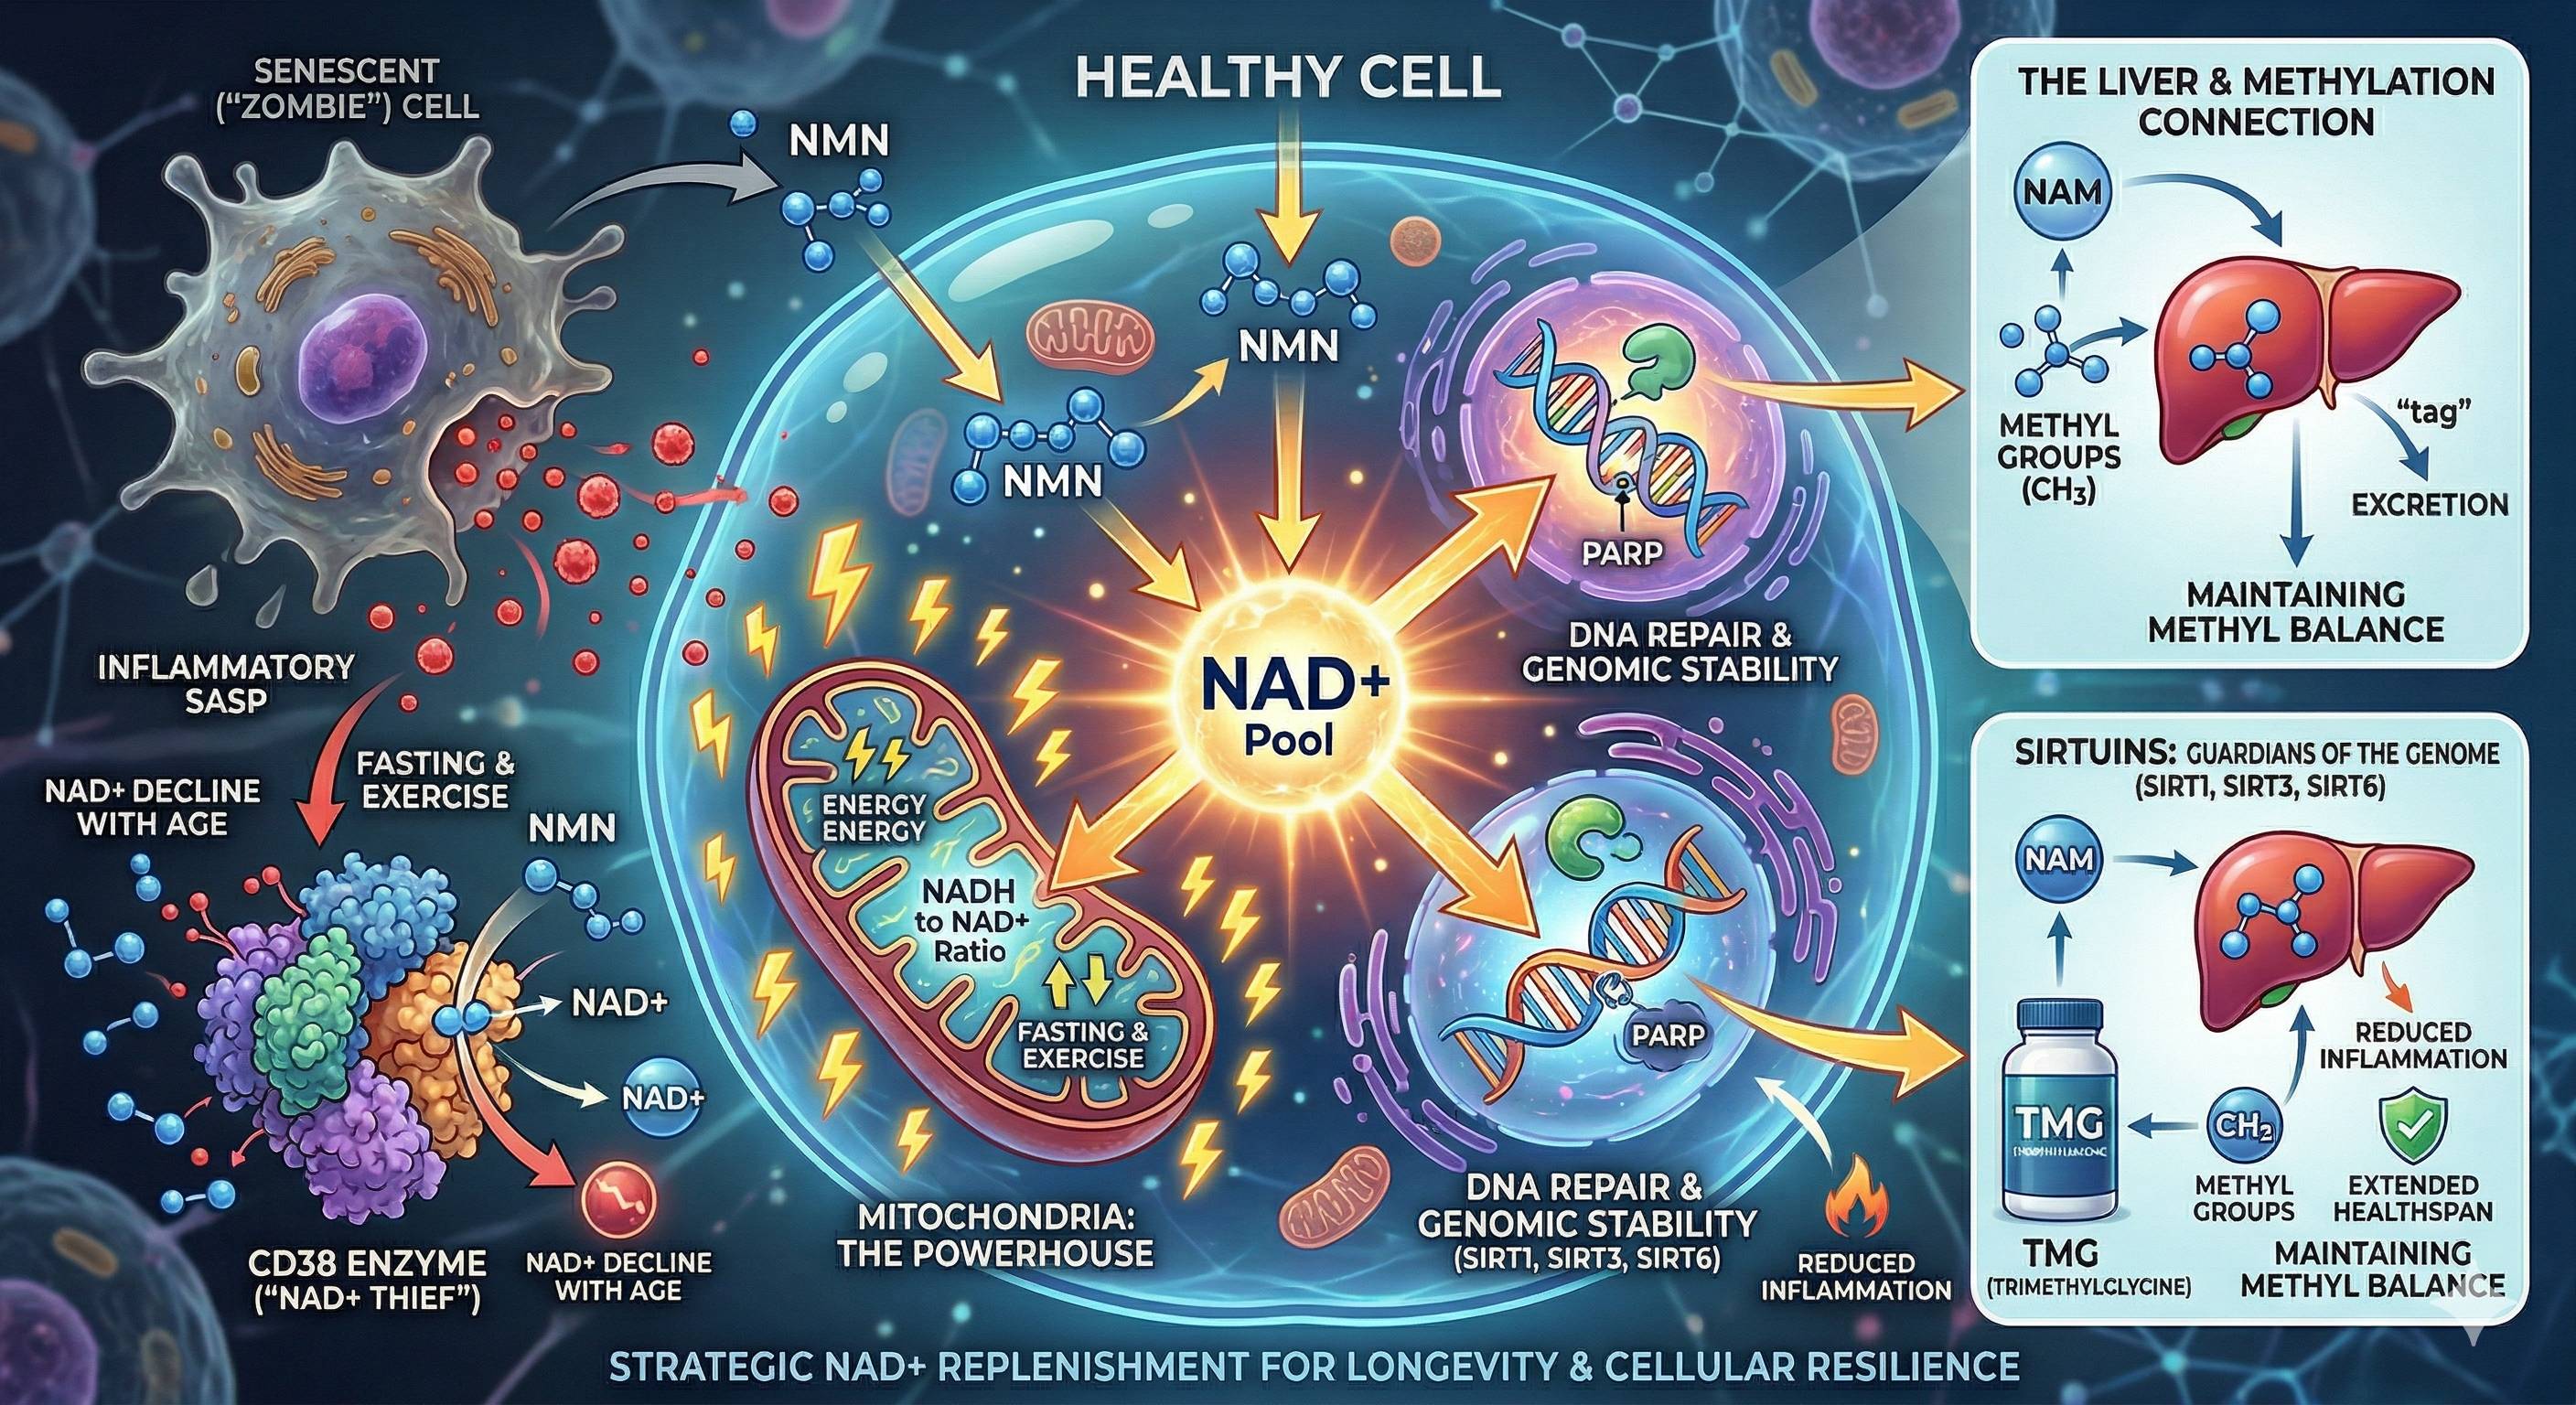
How NMN Boosts NAD+ LevelsNMN is essentially a "building block" for NAD+. The process by which the body converts NMN into NAD+ is relatively direct, making it an efficient supplement for raising levels.
Why Boost NAD+? The Biological BenefitsNAD+ is a "coenzyme" found in every single living cell. It is required for over 500 different enzymatic reactions. Here are the primary reasons why maintaining high NAD+ levels is critical for health:1. Cellular Energy Production (ATP)NAD+ plays a starring role in the mitochondria, the powerhouses of the cell. It acts as an electron carrier in the process of turning nutrients from food into ATP (Adenosine Triphosphate), which is the primary energy currency of the body. Without enough NAD+, cellular energy production falters, leading to fatigue and decreased metabolic function.2. DNA Repair and StabilityOur DNA is constantly under attack from UV radiation, pollutants, and metabolic byproducts. To fix this, the body uses enzymes called PARPs (Poly ADP-Ribose Polymerases). These enzymes are strictly "NAD+-dependent," meaning they cannot function without consuming NAD+. By boosting NAD+, you provide the fuel necessary for cells to repair genetic damage effectively.3. Activation of Sirtuins (The "Longevity Genes")Sirtuins are a family of proteins responsible for cellular health, aging, and DNA protection. They are often called "guardians of the genome."
4. Metabolic Health and Insulin SensitivityResearch indicates that increasing NAD+ through NMN can improve glucose metabolism and insulin sensitivity. This is particularly relevant for maintaining a healthy weight and reducing the risk of age-related metabolic disorders.5. Circadian Rhythm RegulationNAD+ levels fluctuate throughout the day and help regulate the body’s internal clock (the circadian rhythm). Maintaining healthy levels helps ensure that your cells know when to be active and when to undergo repair, which can improve sleep quality and daytime alertness.Note: While NMN is widely studied in animal models with promising results regarding lifespan and healthspan, human clinical trials are ongoing to fully confirm long-term efficacy and optimal dosage. Always consult a healthcare professional before starting new supplements. Furthermore:While the basics of NMN and NAD+ focus on energy and aging, there is a much deeper layer to this "master molecule" that involves cellular theft, "zombie" cells, and the critical importance of a process called methylation.Here are the vital pieces of the NAD+ puzzle that aren't usually mentioned: 1. The "NAD+ Thieves": CD38 and InflammationBoosting NAD+ with NMN is only half the battle; the other half is stopping the "thieves" that steal it.
2. The Methylation Connection (Why you need TMG)This is perhaps the most important practical detail for anyone taking NMN.
3. The "Double-Edged Sword" of CancerNAD+ is essential for all living cells, including cancer cells.
4. Regulatory Status (The 2026 Update)The legal status of NMN has been a rollercoaster. In late 2022, the FDA initially ruled that NMN could not be marketed as a supplement because it was being investigated as a drug. However, as of late 2025, the FDA issued updated guidance essentially reinstating NMN’s status as a legal dietary ingredient, clearing the way for its continued sale in the U.S.5. Natural Boosters and "Sirtuin Activators"Supplementing NMN is just one way to boost the system. You can also:
Are you planning to focus your blog post on the anti-aging benefits for a general audience, or would you like to lean more into the technical "biohacking" side of science?
(https://vitanetonline.com:443/forums/Index.cfm?CFApp=1&Message_ID=6636) Leaky Gut vs. The Postbiotic Fortress: Strengthening Your Microbiome Shield
Date:
February 20, 2026 01:50 PM
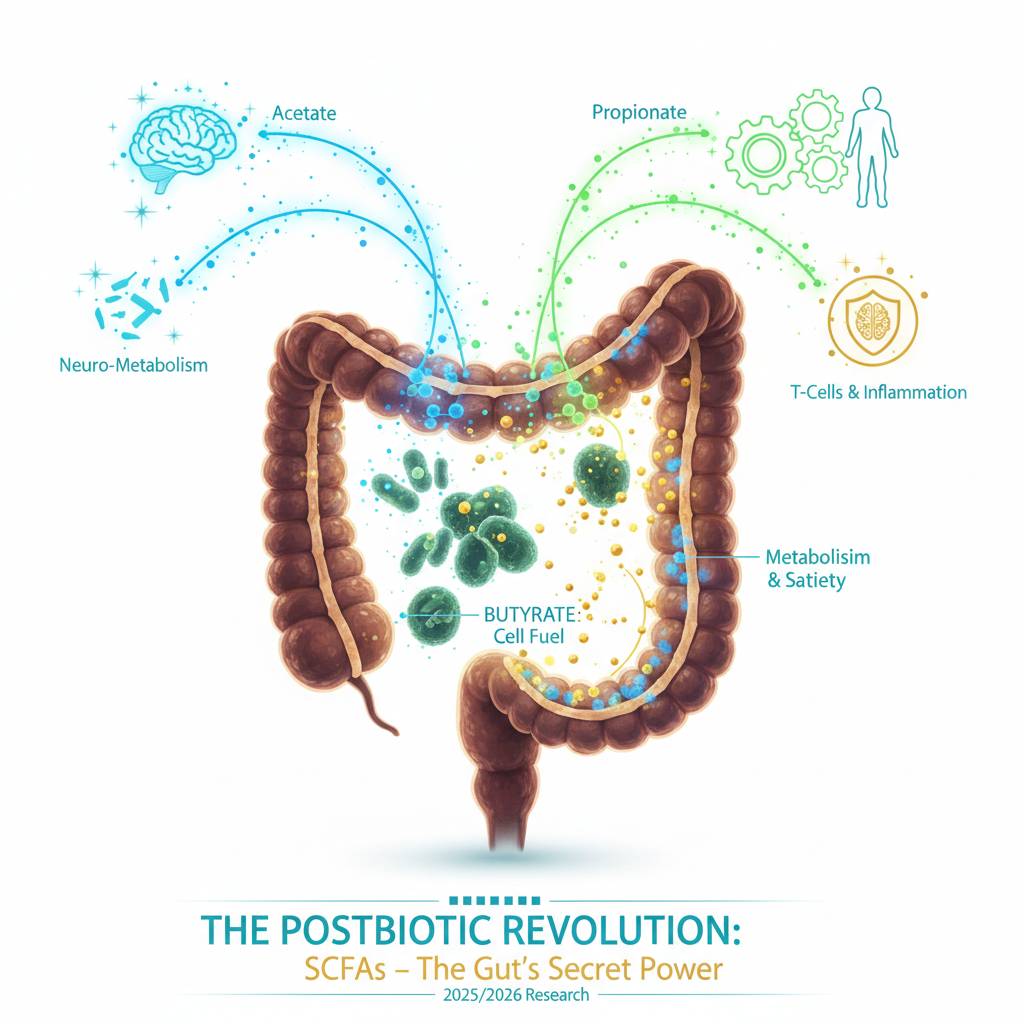
The "Postbiotic" Revolution: Why Your Gut’s Waste is Its Best AssetFor years, the conversation around gut health was a two-player game. You had Prebiotics (the fiber-rich "fuel") and Probiotics (the "live bacteria"). But in 2025 and 2026, the scientific community has pivoted to the third and most important piece of the puzzle: Postbiotics.While we’ve long obsessed over the "tenants" living in our gut, we are finally realizing that it’s their work - specifically the chemical metabolites they produce - that actually runs the show. Postbiotics, particularly Short-Chain Fatty Acids (SCFAs) like Butyrate, Propionate, and Acetate, are the actual "workers" that translate bacterial activity into human health. The Big Three: Acetate, Propionate, and ButyrateWhen you eat a high-fiber meal, your microbiome ferments those fibers into SCFAs. These aren't just waste products; they are high-powered signaling molecules that act like a Wi-Fi signal between your gut and the rest of your body.
Feeding the Gut from the Inside OutMost cells in your body get their energy from the bloodstream. Your colonocytes (the cells lining your large intestine) are different. They are the only cells in the human body that prefer to eat "locally."Butyrate serves as the primary fuel source for these cells, providing up to 70% of their total energy requirements. Research from late 2025 emphasizes that without adequate butyrate, colon cells undergo a form of "cellular starvation," leading to a breakdown in the gut barrier—often referred to as "leaky gut." By "feeding" these cells from the inside, butyrate ensures the intestinal wall remains a tight, fortress-like seal against toxins. 2025/2026 Research: The Signaling RevolutionThe most exciting shift in recent research (2025-2026) is the discovery of how these metabolites act as "systemic messengers." They don't just stay in the gut; they enter the bloodstream and talk to your most vital systems:
Why Postbiotics are the FutureThe beauty of postbiotics lies in their stability. Unlike probiotics, which can die on the shelf or in your stomach acid, postbiotics are heat-stable and have a predictable impact.We are moving away from the "spray and pray" method of taking random bacteria and toward a precision model: delivering the specific metabolites your body needs to thrive. The "Postbiotic" Revolution marks a pivotal shift in gut health, moving beyond live bacteria to focus on the powerful metabolites they produce, specifically Short-Chain Fatty Acids (SCFAs) like Acetate, Propionate, and Butyrate. While 2025/2026 research highlights how these molecules act as systemic messengers - regulating neuroinflammation in the brain and triggering natural satiety hormones like GLP-1 - the most critical scientific breakthrough remains the role of Butyrate as the primary energy source for colon cells. By fueling colonocytes from the inside out, these postbiotics maintain the integrity of the gut barrier and serve as the "actual workers" that translate microbial activity into tangible improvements for the immune system and metabolism.
(https://vitanetonline.com:443/forums/Index.cfm?CFApp=1&Message_ID=6631) Can Cannabis Actually Kill Cancer Cells In The Brain?
Date:
July 26, 2017 04:14 PM
Medical Marijuana use is no longer new. Many of us are aware of a loved one that has benefited from the pain-relieving qualities of the drug, even in advanced and serious conditions, like cancer. What may be less well known, or so far understood, is that it appears that Marijuana may be a potent adversary even against aggressive brain cancers. Recent pharmaceutical research suggests research participants using the drug experienced a significantly prolonged rate of survival over non-users. This intriguing and hopeful research ties in handily with earlier research on rodents that shows the drug as having significant anti-tumor effects, such as inhibiting the growth of the malignancies, besides blocking the growth of new cells and ancillary blood vessels needed by the tumor. Also positive was the discovery that cannabis appears to make the use of chemotherapy more effective for brain cancer patients. Key Takeaways:
"Earlier this year, in what was heralded as a breakthrough for cancer research, GW Pharmaceuticals announced positive results from a study using a combination of cannabidiol and tetrahydrocannabinol to treat an aggressive form of brain cancer." Read more: https://thefreshtoast.com/cannabis/can-cannabis-actually-kill-cancer-cells-in-the-brain/
(https://vitanetonline.com:443/forums/Index.cfm?CFApp=1&Message_ID=5041) Sitting at your desk doesn’t have to be a pain in the neck
Date:
December 25, 2016 02:59 PM
Sitting all day at the desk may be what is necessary for your job, but it may cause pain. This does not have to be how it is, there can be a healthy way to sit at the desk and not feel the constant ache and pain. Read on to see the tips. Key Takeaways:
"In addition to straining joints and muscles in your neck and shoulders, the pressure affects your breathing and mood." Reference: //www.mayoclinic.org/sitting-at-your-desk-doesnt-have-to-be-a-pain-in-the-neck/art-20269947
(https://vitanetonline.com:443/forums/Index.cfm?CFApp=1&Message_ID=3700) Hemp Protein Expected to Be Biggest Emerging Market by 2026
Date:
December 21, 2016 02:59 PM
Hemp protein is a nutrient that has been gaining popularity. Due to its diverse profile of protein, carbohydrates, fatty acids, and fiber, hemp protein has a lot of benefits. It contains all essential amino acids needed by humans and can help with constipation, diabetes, and heart disease. This plant is also very easy to grow without the aid of fungicides or herbicides. Once the benefits of this produce become more widely known, the market is expected to take off. Key Takeaways:
"Hemp protein refers to the industrial by product of hemp seeds. Hemp seeds have a composition of approximately 45 percent oil, 35 percent protein and 10 percent carbohydrates." Reference:
(https://vitanetonline.com:443/forums/Index.cfm?CFApp=1&Message_ID=3683) KudZu, Treatment of alcohol dependence or alcohol abuse 
Date:
May 19, 2005 09:29 AM
For millennia, folk medicines have been used to treat ‘‘alcohol addiction’’ in China. A thorough literature search of the ancient Chinese pharmacopoeias revealed a long list of traditional remedies, including the 16 ‘‘stop-drinking’’ formulae of Sun Simiao (ca. 600 AD) and the ‘‘anti-alcohol addiction’’ formula of Li Dongyuan (ca. 1200 AD), 2 of the most reputed ‘‘medical doctors’’ in the history of Traditional Chinese Medicine. However, like those discovered by the ancient Romans,11 most of the ancient Chinese remedies for ‘‘alcohol addiction’’ were based on psychological aversion: to deter patients from further drinking by associating alcohol drinking with an unpleasant experience. Interestingly, as time went by, treatments based solely on psychological aversion were gradually eliminated from the ancient Chinese pharmacopoeias, presumably because of their ineffectiveness and/or undesirable side effects. The only remedies that have survived this historical trial-anderror scrutiny are those consisting the root (Radix puerariae, RP) or flower (Flos puerariae, FP) of Pueraria lobata (a medicinal plant known to the West as kudzu). It was on the basis of this historical backdrop, we initiated the search of safe and efficacious anti-dipsotropic (alcohol intake suppressive) agents from RP. This approach has led to the discovery of daidzin,12 an isoflavone that has since been shown to reduce alcohol drinking in all alcohol preferring animal models tested to date.
Alcohol abuseAlcohol abuse and alcohol dependence (i.e., alcoholism) are serious public health problems of modern society. In the United States alone, an estimated 13 million adults exhibit symptoms of alcohol dependence due to excessive alcohol intake, and an additional 7 million abuse alcohol without showing symptoms of dependence according to U.S. Government projections from studies conducted in the mid-1980s. Alcohol dependence and abuse are very expensive: in economic and medical terms, it will cost the U.S. well over $200 billion in 1991 with no prospect of falling or leveling off. The social and psychological damages inflicted on individuals as a consequence of alcohol abuse, e.g., children born with fetal alcohol syndrome (FAS) and victims of alcohol-related accidental death, homicide, suicide, etc., are immense. While it is generally accepted that alcoholism and alcohol abuse are afflictions with staggering international economic, social, medical, and psychological repercussions, success in preventing or otherwise ameliorating the consequences of these problems has been an elusive goal. Only very recently the public view that alcoholism and alcohol abuse are remediable solely by moral imperatives has been changed to include an awareness of alcoholism and alcohol abuse as physiological aberrations whose etiology may be understood and for which therapy may be found through scientific pursuits. Both alcohol abuse and dependence arise as a result of different, complex, and as yet incompletely understood processes. At present, alcohol research is in the mainstream of scientific efforts. Our studies on alcohol (ethanol or ethyl alcohol) have been based on the hypothesis that its abuse can ultimately be understood and dealt with at the molecular level. Such a molecular understanding, if achieved, would provide a basis for the identification and development of appropriate therapeutic agents. Our view hypothesizes that the clinical manifestations of alcoholism and alcohol abuse are the consequence of aberrations or defects within one or more metabolic pathways, affected by the presence of ethyl alcohol. In order to test this hypothesis, our initial studies focused on physical, chemical, and enzymatic properties of human alcohol dehydrogenase (ADH), the enzyme that catalyzes alcohol oxidation according to the following reaction formula: CH.sub.3 CH.sub.2 OH+NAD.sup.+ .fwdarw.CH.sub.3 CHO+NADH In addition, our studies more recently have focused on the aldehyde dehydrogenases (ALDH) which catalyze the subsequent step in the major pathway of ethanol metabolism according to the following reaction formula: CH.sub.3 CHO+NAD.sup.+ .fwdarw.CH.sub.3 COOH+NADH Prior to our research (for example, see Blair and Vallee, 1966, Biochemistry 5:2026-2034), ADH in man was thought to exist in but one or two forms, primarily in the liver, where it was considered the exclusive enzyme for the metabolism of ethanol. Currently, four different classes of ADH encompassing over twenty ADH isozymes have been identified and isolated from human tissues. There is no reason to believe that all of these ADH isozymes are necessary to catalyze the metabolism of a single molecule, ethanol, even though all of them can interact with it. We have proposed that the normal function of these isozymes is to metabolize other types of alcohols that participate in critical, physiologically important processes, and that ethanol interferes with their function (Vallee, 1966, Therapeutic Notes 14:71-74). Further, we predicted that individual differences in alcohol tolerance might well be based on both qualitative and quantitative differences in isozyme endowment (Vallee, 1966, supra).
Our research has established the structures, properties, tissue distribution, and developmental changes for most of the ADH isozymes, which while structurally quite similar, and presumed to have evolved from a common precursor, are functionally remarkably varied. Of the more than 120 publications from our laboratory that relate to the above subjects, the following, arranged in six categories, are especially useful for instruction in the prior art.
Kudzu Recovery 60ctKudzu Recovery 120ct
Kudzu Root Extract 50capsKudzu Root Extract from Solaray 60ct
(https://vitanetonline.com:443/forums/Index.cfm?CFApp=1&Message_ID=79) | |||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||